
Medical history
My name is Hans Keller.
I am 60 years old and work as a teacher. For about an hour I have had chest pain, directly behind the sternum. The pain radiates to the left shoulder. I suddenly broke out in cold sweat and felt very anxious.
The pain started very suddenly, without me noticing any specific trigger. I had not exerted myself physically nor eaten beforehand.
I can breathe normally and I do not have a cough. I did not faint. I also do not have fever or palpitations. I have noticed no weakness or numbness, and I can see and speak normally.
As far as I know, I do not have high blood pressure, diabetes, or elevated cholesterol. There are no known heart attacks or strokes at a younger age in my family. I do not smoke.
I am covered by statutory health insurance and came here alone.
I weigh about 85 kilos.
Mr. Hans Keller
The 60-year-old patient presented with acute retrosternal chest pain of about one hour’s duration with radiation to the left shoulder. He reported accompanying cold sweat and pronounced anxiety. There was no anamnestically reported association with physical exertion or food intake.
Dyspnea, cough, syncope, fever, palpitations, and focal neurological symptoms were denied.
Anamnestically there was no arterial hypertension, no diabetes mellitus and no dyslipidemia known. Nicotine use was denied. Family history regarding premature cardiovascular events was unremarkable.
The patient works as a teacher and is covered by statutory health insurance. He presented without an accompanying person.
Weight: 83 kilos
Signature
00/00/0000
Vital signs
-
Blood pressure: 140/90 mmHg
-
Heart rate: 88/min
-
Oxygen saturation (SpO2): 97% on room air
-
Respiratory rate: 18/min
-
Body temperature: 36.7 °C
-
Blood glucose: 112 mg/dl
Suspected diagnosis
High-grade suspicion of an acute coronary syndrome in a patient with one hour of retrosternal chest pain radiating to the left shoulder, cold sweat and anxiety.
-
Transfer the patient immediately to a monitored emergency department bed. Physical rest; no independent mobilization.
-
Obtain a 12-lead ECG immediately and present it to a physician without delay. Perform the following measures in parallel; do not delay the ECG because of them.
-
Connect continuous ECG and SpO2 monitoring. Check blood pressure every 5 minutes during initial care. Keep a defibrillator immediately available.
-
Place a peripheral venous access, preferably 18 G. Draw blood: hs-troponin, blood count, sodium, potassium, magnesium, creatinine/eGFR, glucose, INR and aPTT. Schedule a second hs-troponin draw after 1 hour according to the laboratory procedure used.
-
Pain intensity: NRS 8/10. Elicit current medications, allergies and bleeding history. Perform a focused physician examination in parallel, including assessment for signs of aortic dissection.
-
Prior aspirin intake was denied. Have aspirin 300 mg p.o. chewed once, provided there are no contraindications. Document dose and time of administration.
-
No oxygen administration with current SpO2 of 97% on room air.
-
For analgesia, give morphine 2.5 mg slowly i.v. due to ongoing chest pain, under monitoring of blood pressure, respiratory rate, SpO2 and level of consciousness. Do not delay the immediate ECG because of this.
-
Nitroglycerin, anticoagulation and P2Y12 inhibitors should be ordered specifically only after immediate physician review of the ECG and checking for respective contraindications.
-
Inform the responsible senior physician or cardiology service now about the high-grade ACS suspicion.
ECG
Interpretation
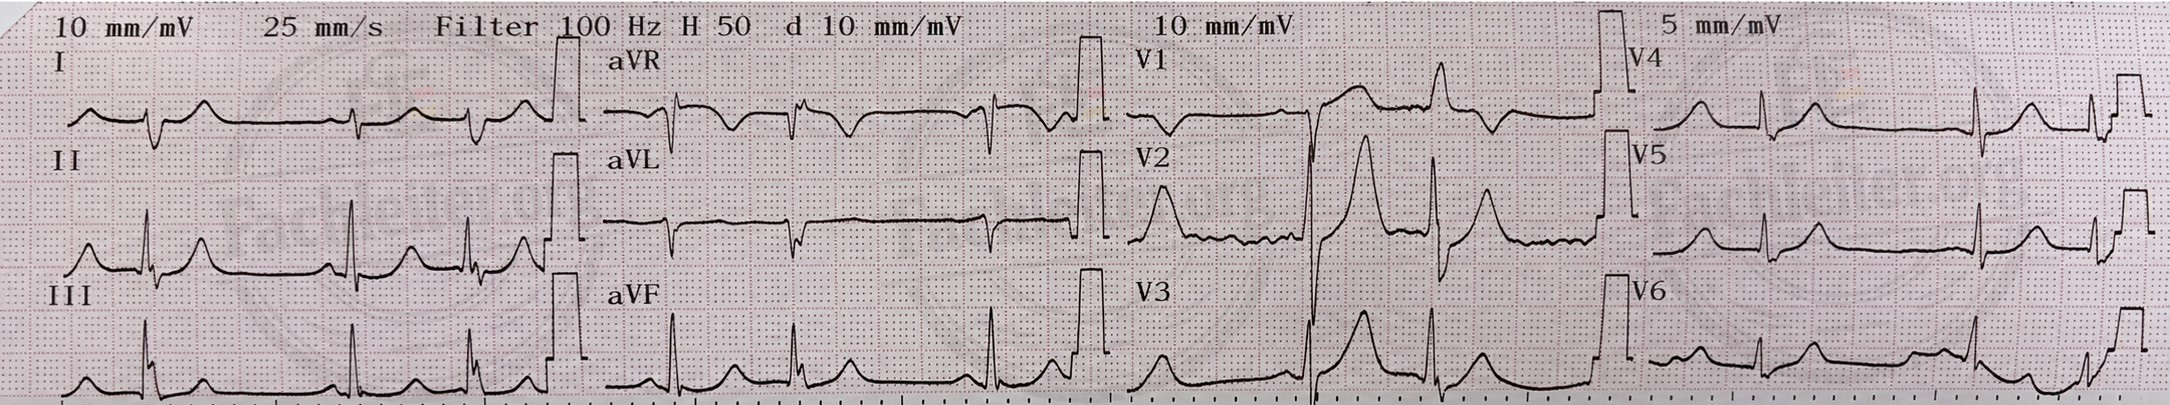
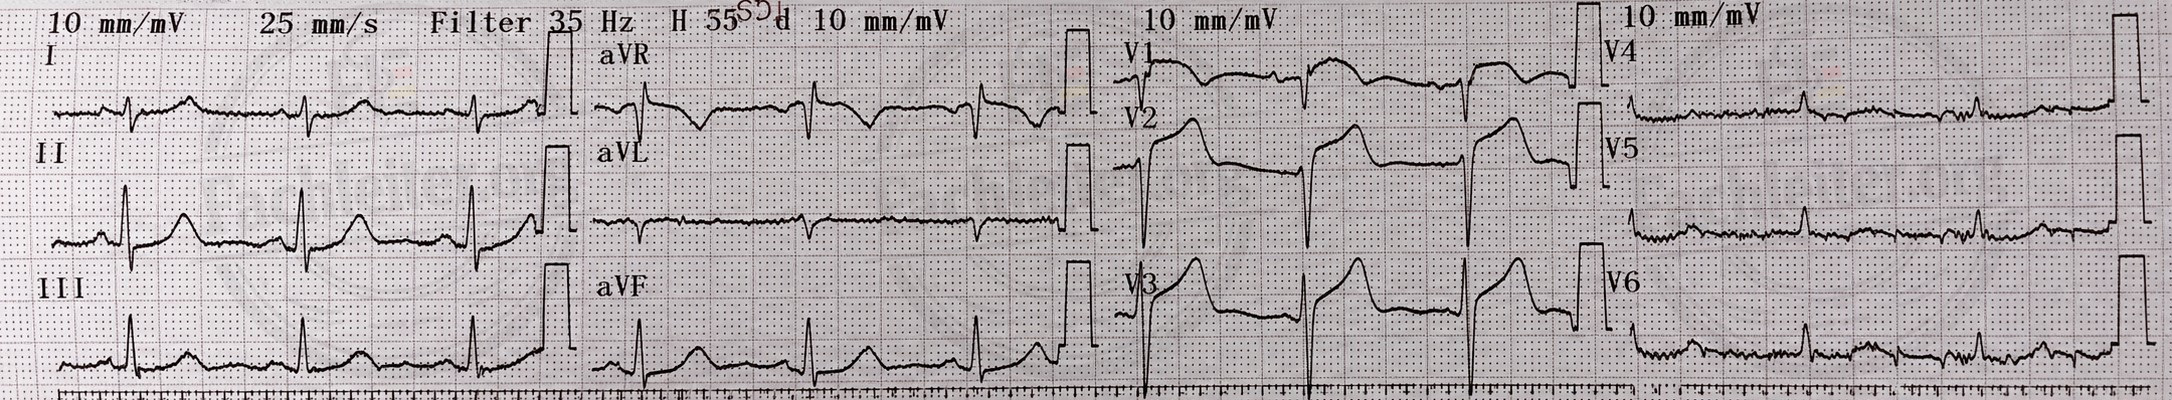
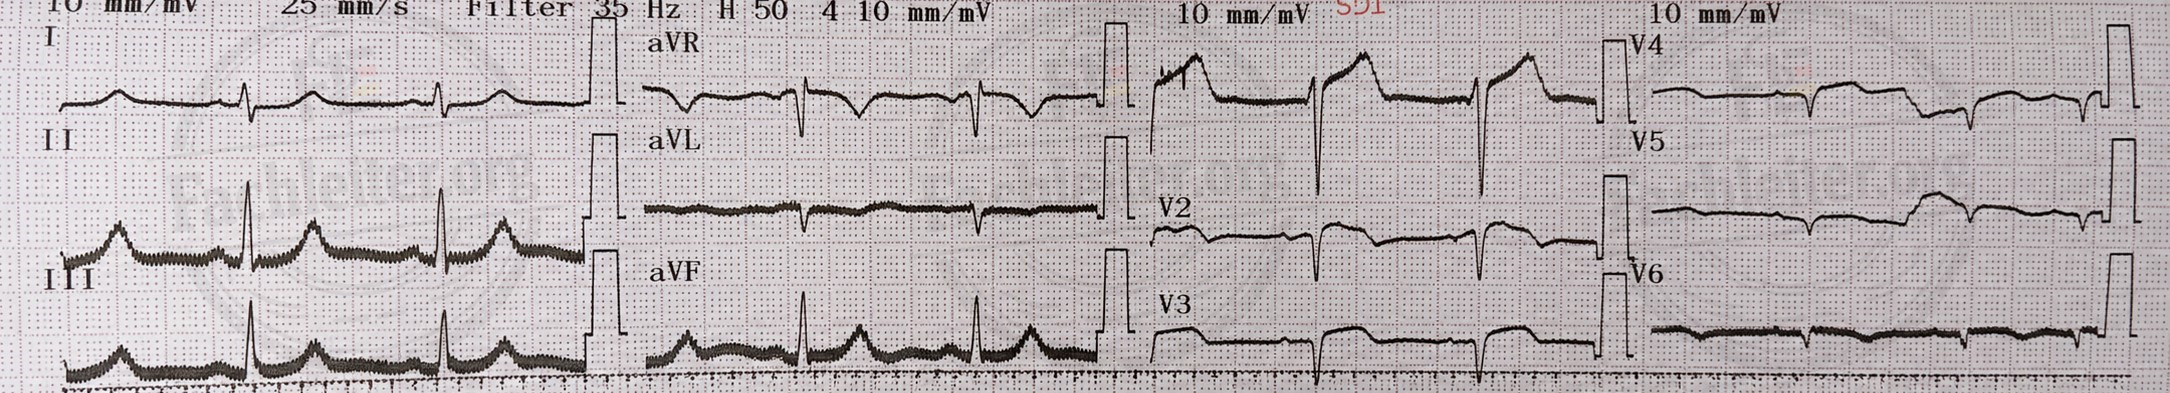
The 12-lead ECG of Mr. Keller from DD.MM.YYYY at HH o’clock was recorded at a paper speed of 25 mm/s and a calibration of 10 mm/mV. Artifacts are present.
It shows sinus rhythm with a heart rate of 75/min and ventricular extrasystoles. In addition, there is ST-segment elevation in aVR and disturbed R-wave progression across the precordial leads.
In the subsequently recorded additional ECG tracings, ST-segment elevations are also present.
A definitive vessel assignment is made by coronary angiography.
However, in suspected right ventricular infarction nitroglycerin should not be given, as preload reduction can trigger a pronounced blood pressure drop.
Further management
Working diagnosis: acute STEMI with anterior and posterior involvement with typical symptoms and corresponding ECG findings.
Body weight: 83 kg.
Vital signs: BP 140/90 mmHg, heart rate 88/min, SpO2 97% on room air, respiratory rate 18/min.
After telephone discussion with the cardiology senior physician of the PCI center, immediate transfer for emergency coronary angiography with primary PCI was agreed. The catheterization team is activated. Transport time is approximately 30 minutes.
-
Organize emergency transport with paramedic accompaniment without delay. Arrange direct handover in the catheterization laboratory. Do not wait for troponin results. Document time of diagnosis, acceptance and departure time.
-
Continue continuous ECG and SpO2 monitoring. Monitor blood pressure every 5 minutes until handover and after any hemodynamically active medication. Ensure defibrillation readiness throughout care and transport.
-
Check existing venous access for patency. Place a second peripheral access if this does not delay departure.
-
Unfractionated heparin 5,810 (rounded 6000) IU i.v. once as a bolus corresponding to 70 IU/kg. Check for prior anticoagulation, relevant bleeding and known HIT beforehand. Document dose and time of administration and communicate to the cath lab team. Further dosing in the cath lab according to ACT.
-
Ticagrelor 180 mg p.o. once for loading per agreement with the PCI center. Check contraindications, especially active bleeding or prior intracranial hemorrhage, and whether a P2Y12 inhibitor has already been given.
-
Atorvastatin 80 mg p.o. as the first dose, provided there are no contraindications. Do not delay departure because of this.
-
Reassess pain intensity using NRS. If severe chest pain persists, give morphine 2 mg slowly i.v. under physician supervision. Then check pain intensity, blood pressure, respiratory rate and level of consciousness. Further titration only after renewed physician assessment.
-
No oxygen administration at SpO2 97% on room air. No routine fluid bolus with currently stable circulation. Until exclusion of right ventricular involvement, do not give nitrates initially.
-
Perform additional diagnostics only if this does not delay transfer. In particular, do not delay for echocardiography or pending laboratory results.
-
Provide ECG tracings, brief report, available laboratory results, allergy information and all medication doses and times. Report outstanding results subsequently.
-
At departure transmit current vital signs and estimated arrival time to the PCI center. Provide a structured personal handover to the accompanying emergency physician.
Laboratory
| Laboratory parameters | Value |
|---|---|
| hs-troponin T on admission | 86 ng/l |
| Hemoglobin | 14.6 g/dl |
| Leukocytes | 10.8 G/l |
| Platelets | 248 G/l |
| Sodium | 139 mmol/l |
| Potassium | 4.2 mmol/l |
| Magnesium | 0.84 mmol/l |
| Creatinine | 0.96 mg/dl |
| eGFR | 91 ml/min/1.73 m² |
| Glucose | 142 mg/dl |
| CRP | 3.2 mg/l |
| INR | 1,0 |
| aPTT | 29 s |